Why Use STPA?

The real-world evidence from industry adoption of System-Theoretic Process Analysis (STPA)

New to STPA?What is STPA?STPA in Depth

Briefing your leadership?Slides and Briefings

Page Overview

The Evidence

  1. 1
    Evidence from Industry: STPA Benefits

    Published comparisons of STPA with FMEA, FTA, HAZOP, and other methods, and what the authors concluded.

  2. 2
    Level of Effort vs. Outcome

    Hours spent on STPA and on traditional methods for the same systems, and what the analyses found.

  3. 3
    Why Are Organizations Using STPA?

    Case studies from many industries, grouped by benefit.

Making the Case

  1. 4
    The Cost of Finding Flaws Late

    The cost of fixing a flaw grows the later it is found.

  2. 5
    Briefing Your Leadership

    Executive slides to download, or a briefing we tailor for your organization.

Part 1 · The Evidence

Evidence from Industry: STPA Benefits

Highlights from the studies on this page, which are a small sample of the many published comparisons of STPA with other methods.

30×less effort than the standard methods on the U.S. Ballistic Missile Defense System: about 960 hours, against 28,800
2 weeksof STPA by one analyst found the cause of a medical device recall that a year of FMEA had missed
53causes found by STPA that FMECA missed, in an electric power steering design
19findings in the table below, most from comparisons of STPA with FMEA, FTA, HAZOP, and other methods
Core ClaimDocument LinkSTPA Conclusion
More Complete RequirementsAssuring Safety of NextGen Procedures“STPA found more potential causes of the hazard considered ... identified nineteen safety requirements that were not in either of the two official NextGen documents.”
More EfficientIntegrating STPA in Large Organizations“STPA provided requirements at multiple levels more efficiently than a system element fault analysis did ... effective in finding missing requirements especially early in concept phase.”
Finds Software and Interaction HazardsComparison of the FMEA and STPA safety analysis methods“With regard to component failure hazards, FMEA identified more component failure hazards than STPA. With regard to software error type hazards, STPA found more hazards than FMEA of unique hazards. With regard to component interaction error type hazards, STPA found some hazards; however, FMEA did not find any of unique hazards.”

Checked step by step, this STPA departs from the method in several places, and its analysts had limited experience in the domain. Even so, STPA found software and component-interaction hazards that the experienced FMEA analyst did not.
More EffectiveJAXA Evaluation of STPA“Because the HTV was originally developed using fault tree analysis and following the NASA standards for safety-critical systems, the results of our ... STPA can be compared.”

“STPA identified the failures in the existing fault tree analysis but STPA also identified additional causal factors which had not been identified in the existing FTA.” Most of the STPA insights were related to system design flaws and to software.
Found Flaws the Standard Analysis MissedSTPA for the Ballistic Missile Defense System

Software Challenges in Achieving Space Safety
“STPA found so many flaws during just a limited three-month analysis that deployment was delayed for six months to fix the newly identified hazardous scenarios.”
More Effective/EfficientHazard Analysis of Collision Avoidance System Using STPA“STPA has proved to be an effective and efficient hazard analysis method for assessing the safety of a safety-critical system.”

“The reason for the effectiveness of STPA is that it considers and greatly focuses on the control commands or events and their feedbacks … instead of focusing on individual component failures.”

“Our positive experiences with STPA suggest that performing both steps 1 and 2 in a group of both domain experts and risk analysts increase the discussion opportunities and lead to a more effective process and more in-depth results. We experienced that the identified risks and hazards had more technical depth and constituted a better view on the analyzed system safety.”
More Scalable with ComplexityHazard Analysis: Application of STPA to Ship-to-Ship Transfer“A traditional hazard analysis tool, such as HAZOP or FMEA, cannot investigate the lack of complex systems properly ... STPA is established to evaluate the safety of such complex systems.”
More DescriptiveApplying STPA in Development of Autonomous Container Handling Machinery“STPA emphasizes consideration of the context ... leading to more descriptive scenarios than HAZOP... HAZOP focuses only on deviations, whereas STPA also looks at issues in the intended operation.”
More EffectiveRegulator Evaluations...Catastrophic design flaws were found by STPA, including conditions that would cause dual engine shutdowns. The traditional methods (e.g., FHA, FTA) had missed these scenarios. The STPA results were not widely disseminated at the time. A few years after the STPA results, the exact scenarios started happening in operation. The fix was to implement the STPA-generated technical requirements from years prior.
Less Time RequiredEPRI Nuclear StudySTPA took less time and fewer resources to perform than traditional methods.
More EffectiveComparing STPA and FMEA“Of the 137 causes found by STPA, 53 causes were not covered by FMECA.” Many of the STPA insights involve software behavior and flawed interaction.
Applicable EarlySTPA for ISO26262“STPA is a top-down process and the detailed design of item is not necessary to be known before applying STPA to the item.”
“We believe that STPA can support the HARA process in ISO 26262 activities and help the functional safety engineers to develop the functional safety requirements for each item identified at an early stage in the concept phase based on the results of the STPA.”
Applicable EarlyA Systems-Theoretic...“By starting the STPA analysis early in the development process at a high level of abstraction, a wide variety of different types of scenarios can be identified.”
Higher Return on InvestmentWhen STPA Results Surprise You“STPA cost for this application: $2,400. Value added: Identifying and addressing the $1m design flaw. ROI: 416.”
More Effective for SecuritySystem-Theoretic Process Analysis for Security (STPA- Sec)“Generate more scenarios with more interactive complexity ... STPA-Sec scenarios help identify functional vulnerabilities [and additional] successful attacks that will delay pulse feedback.”
More GuidanceApplication of STPA in Radiation Therapy: a Preliminary Study“STPA offers more guidance in understanding human-related hazards ... STPA adds new hazards and safety-related recommendations to existing HFMEA results.”
STPA for Compliance with ISO26262Using STPA in ISO26262Compared to HARA, STPA is strong on Human Error, Software failure, Interaction failure, and Environmental Error.
More EffectiveEmpirical Evaluations of STPA in the Aviation Industry“STPA identified 30 additional scenarios that were missed w/ standard methods [in certified engine control]... The TCM flaws exactly match the STPA findings by other teams years earlier.”
More Complete RequirementsSafety Assessment of Complex, Software-Intensive Systems“Improves upon the human-system interaction aspect of safety assessment... We illustrate the effectiveness of this new methodology by an analysis of the NextGen ‘In-Trail Procedure in Oceanic Airspace’ ... STPA derives some additional safety requirements beyond those in the Operational Safety Analysis (OSA) of DO-312.”

Part 2 · The Evidence

Level of Effort vs. Outcome

Effort on the Same System: Traditional Analysis and STPA

Traditional analysisSTPA

  1. Space Autonomous Vehicle~170 vs ~4,000 hours (FTA)
  2. Medical Diagnostic Device~50 vs ~275 hours (FMEA)
  3. Process Digital Control System Upgrade12–32 vs 120 hours (HAZOP); FMEA took 1,000+
  4. Aviation Aircraft AMS3.5 months vs 1–2 years (AFHA, SFHA, PSSA, CCA)
  5. Automotive Valeo Range Extender1/3 of the effort (FTA and CPA)
  6. Automotive Electric Power Steering~6 months vs ~1 year (FMECA)
  7. Nuclear High Pressure Coolant InjectionNo hours givenDays vs weeks (FTA, PRA, FMEA, HAZOP)
Each row is one study. The grey bar is the effort of the traditional analysis, and the blue bar is STPA’s effort on the same system. If a study gives a range, the blue bar uses the figure least favorable to STPA. The table below gives the sources and what each analysis found.
IndustryDocument LinkTraditional Method EffortSTPA EffortOutcome/Efficiency Gain
ProcessDigital Control System UpgradeHAZOP: 120 Hours
FMEA: 1,000+ Hours
Team 1: 32 Hours
Team 2: 12 Hours
STPA 4x faster (minimum) in every trial
STPA caught hidden flaw others missed
STPA produced 0-cost solution others missed
AutomotiveValeo Range Extender3x Effort of STPA1x EffortSTPA took 1/3 the effort and found 2 safety constraints for the inverter software that CPA and FTA missed
SpaceAutonomous VehicleFTA: Months/Years ~4000 HoursWeeks/Months ~170 HoursSTPA found all FTA causes + interactions + software flaws
AutomotiveElectric Power SteeringFMECA: ~1 Year~6 MonthsSTPA found 53 causes missed by FMECA
MedicalDiagnostic DeviceFMEA: Months/Years ~275 hours2 Weeks
~50 hours
Reduced analysis time by >90%
Found recall cause
AviationAircraft AMSAFHA, SFHA, PSSA, CCA: ~1-2 Years3.5 MonthsSTPA generated missed requirements
STPA reduced cost by preventing late rework
NuclearHigh Pressure Coolant InjectionFTA/PRA/FMEA/HAZOP: WeeksDays
“Much less time”
STPA was only method to find the actual accident scenario

Part 3 · The Evidence

Why Are Organizations Using STPA?

Organizations are adopting STPA because of the growing evidence from industry about its advantages. The evidence comes mostly from real-world case studies and comparisons.

Three Benefits Shown by Industry Studies

  1. 1STPA is more effective.See the evidence
  2. 2STPA takes less time to apply.See the evidence
  3. 3STPA finds flaws earlier, minimizing the cost to fix them.See the evidence

Benefit 1 · Evidence

STPA Is More Effective

Cooling System: A Flaw Every STPA Team Found, and FTA, FMEA, and HAZOP Missed

An extensive comparison study was performed on the product’s cooling system. The system involved a digital control system (DCS) to manage cooling pumps. A latent design flaw in the logic led to a scenario where the system would inadvertently shut down all cooling, even though all components were operating within their design specifications. That shutdown would mean a costly “Loss of Mission.” A description of the system was given to independent teams, each using different methods to look for flaws in the design and requirements.

Which Teams Found the Cooling-System Flaw
  • STPA: A team of professionals analyzed the system using STPA. They found the flaw in a few hours. This study was replicated seven times, each time with independent teams who had no existing knowledge of the flaw. Some teams only had a few hours of STPA training and no previous experience using STPA. Every STPA team found the flaw.
  • FTA: A team of professionals did not find the flaw. In fact, the team incorrectly concluded that the proposed modification would increase reliability by a factor of 10. In reality, the proposed modification introduced a major weakness involving a missing function that reduced reliability by a factor of 10.
  • FMEA: A team of professionals spent over 1,000 person-hours creating 200+ pages of FMEA documentation. They focused on failure modes like “Sensor fails high”. They did not find the flaw because the flaw only appeared when all sensors were working (not failing). The FMEA did not cover the case in which the sensors correctly report a high flow and the digital controller treats the readings as faulty, because of a missing requirement in its logic.
  • HAZOP: A team of professionals spent 120 person-hours completing a HAZOP study of the system. They analyzed deviations like “High Flow” but dismissed them, believing high flow was beneficial for cooling. They did not find the flaw.

No component or function failed. When both cooling pumps run, as planned every nine months, all three flow sensors correctly read above their range. The controller’s fault detection takes those readings as three faulted sensors and shuts down cooling. STPA asks what the controller would have to believe to shut down cooling when cooling is adequate. That question led every STPA team to the flaw, and to an expected loss of at least $1 million each time both pumps run.
Link to Source

EPRI Nuclear Plant Study: Only STPA Found the Scenario That Had Happened

EPRI (Nuclear Power): In a study of High Pressure Coolant Injection (HPCI) and Reactor Core Isolation Cooling (RCIC) systems, STPA was compared with FTA and FMEA. None of the analysis teams were aware of a specific flaw that had been uncovered recently during operation, but they were all asked to analyze the system to identify potential weaknesses and flaws. Only STPA found the accident scenario that had actually occurred at the plant. The scenario arose from interactions among components and functions that worked as designed, so the FTA and FMEA, which start from component and function failures, did not identify it.

See how EPRI set up the blind test, on STPA in Depth

Link to Source

STPA Evaluation by Aviation Regulators

Subject matter experts from the FAA, EASA, ANAC, ICAO, and NASA evaluated STPA together. They applied STPA to aircraft systems that had already been certified using the standard methods, including FHA, FTA, and FMEA. STPA found catastrophic design flaws, among them conditions that could command both engines to shut down in flight without any component or function failure. The systems had passed certification, so these were flaws the established processes had not found.

Link to Source

Autonomous Vehicles: STPA Compared to ISO 26262 Standard Methods

Abdulkhaleq et al. found that while traditional HARA (e.g., FTA, FMEA, etc.) focuses on failure-based causes, STPA extends this by identifying the specific causal scenarios that could lead to those events, including flaws in the architecture, unsafe interactions between non-failed components, and other factors. This allows engineers to define safety constraints for autonomous functions that do not depend on failure probabilities but are still needed for safe behavior.

Link to Source

Electric Power Steering: STPA Compared with FMECA

A comparative study by Sotomayor and colleagues compared STPA against FMECA in the analysis of an EPS architecture with many software interactions.

What the EPS Comparison Found

  • The Gap: 53 of the causes STPA found were not covered by the FMECA.
  • STPA: Identified 137 potential causes.
  • FMECA: Identified 95 potential causes of hazards.

The causes the FMECA missed clustered around software logic, complex signal interactions, and human-machine interface issues. For example, FMECA identified what would happen if a torque sensor broke. However, it missed scenarios involving algorithm thresholds that no longer match the physical process after extended operation, or a software functionality that would be eliminated because it would never be able to correctly resolve conflicting sensor feedback in certain situations. None of these is a component or function failure. Each is a design feature that becomes hazardous in a particular context, which is the kind of cause STPA looks for when it asks how a control action could be unsafe.

Link to Source

Ballistic Missile Defense System: Hazards Beyond the Military-Standard Analysis

U.S. Missile Defense Agency (MDA) published findings from applying STPA to the Ballistic Missile Defense System (BMDS). A two-person STPA team identified many hazards beyond those in the official military-standard analysis, many of them involving software and logic. Upon reviewing the findings, the contractor agreed with their criticality and delayed the deployment of the system by six months to fix the software flaws, which would have led to inadvertent launches or failure to intercept.

Link to Source

U.S. Navy Dynamic Positioning System: A Scenario STPA Found Before the Collision

U.S. Navy: Following two serious accidents on a vessel with a Dynamic Positioning System, STPA was applied. The official FTA/FMEA had identified component failures, but STPA identified those plus many “non-failure” hazard causes. STPA also identified a scenario involving a complex interaction that had not yet resulted in an accident on that ship. This scenario was ignored by the Navy at the time, but the vessel later collided with a nuclear submarine from the cause STPA had identified. No component or function failed: the thrusters, the sensors, and the computer all worked, and the timing and logic of their interaction under certain environmental loads led to a loss of station-keeping. FMEA and FTA look for components and functions that fail, so they did not identify a scenario in which every component and function worked as designed.

Link to Source

Blackhawk Helicopter: Hazards the Official Analysis Rated Marginal

Blackhawk Helicopter: In a comparison with traditional PHA/FTA/FMEA that was performed, STPA examined a scenario involving the Blackhawk’s control system. The traditional analysis used “average” human error probabilities and deemed certain hazards “marginal”. STPA analyzed the specific information available to the pilot during the scenario and showed that, given the display design, the pilot would systematically make the incorrect decision. The cause of the “error” lay in the design of the human-machine interface, and the analysis identified catastrophic scenarios that the official analysis had rated marginal.

Link to Source

STPA as a Framework for Defining Safety of the Intended Functionality (SOTIF)

The work by Abdulkhaleq and Sotomayor shows that STPA provides a framework for defining the “safety of the intended functionality” (SOTIF). In autonomous systems, hazards often come from a process model mismatch, where the autonomy perceives the world incorrectly, more than from a hardware failure. STPA models what each controller believes about the world, so STPA can examine these mismatches.

Link to Source

STPA Uncovered High-Severity Risks in Clinical Decision Support Systems (CDSS)

Clinical Systems: The “STPA Applied to Healthcare Clinical Decision Support Systems” presentation provides results involving Electronic Health Records (EHR) and decision support. STPA treats the clinician and the software as a control loop, identifying scenarios where “alert fatigue” or poor data visualization leads to unsafe treatment decisions, even when no component or function fails.

Link to Source

Certified Engine Controls: 30 Scenarios the Standard Process Missed

Aviation: In a certified aircraft engine control system, STPA identified 30 catastrophic scenarios missed by standard certification processes (ARP4761), Years later, aircraft in service had dual-engine flameouts from flaws that matched the STPA findings.

Link to Source

NextGen In-Trail Procedure: Requirements Missing from the Official Analysis

NextGen In-Trail Procedure (ITP): The transition to NextGen air traffic control involves shifting responsibility from ground controllers to cockpit automation. Moving responsibility this way creates hazards from interactions among components, which are easy to overlook. Researchers compared STPA results against the official safety analysis (OSA) contained in RTCA DO-312, which relied on fault trees and event trees. STPA identified 19 safety requirements that were not in the official analysis.

Link to Source

JAXA H-II Transfer Vehicle: Hazards Between Controllers That the Fault Tree Missed

Spacecraft Systems (HTV): In the analysis of the JAXA H-II Transfer Vehicle (HTV), STPA was compared with the Fault Tree Analysis that NASA requires. The results show that STPA found a superset of the FTA findings. The “additional hazardous scenarios” found by STPA were primarily located in the interfaces between the multiple controllers: the astronauts, the HTV autonomous software, the NASA mission controllers, and the JAXA mission controllers. Fault trees are built around component and function failures and have difficulty representing the communication and coordination between these controllers. STPA, by modeling the feedback loops and process models of each agent, identified scenarios where conflicting commands or missing feedback could lead to a collision or loss of mission, even if all hardware functioned reliably.

Link to Source

Continental: Hazards in Automated Driving That HARA Missed

A team at Continental applied STPA alongside traditional HARA (FMEA, FTA, etc.) within the ISO 26262 standard for fully automated vehicles. STPA found more because it looks beyond malfunctions, at hazards that arise when the system performs as designed.

Two Causes of Hazards That HARA Missed

  • Unsafe Interactions: The braking system and the steering system fight each other due to conflicting optimization targets.
  • Environmental Error: The sensors see the world correctly, but the world presents a situation the algorithms cannot handle (e.g., perfect reflection of the sun blinding a camera).

Link to Source

STPA Comparison to Existing HFMEA Results in Radiation Therapy

Radiation Therapy, STPA vs. HFMEA: In a comparative study on radiation therapy processes, STPA was compared to Healthcare Failure Mode and Effect Analysis (HFMEA). The study found that while there was overlap, STPA offered “more guidance in understanding human-related hazards.” For instance, HFMEA might identify a hazard as “Radiographer fails to check patient ID.” The corrective action is “Retrain Radiographer.” STPA identified the same hazard but traced the cause to the control structure. It found that the process allowed the “Post-planner to send a plan to the delivery team before it was complete.” This systemic flaw sets the radiographer up for failure. One example of an STPA-generated requirement missing from HFMEA was “System must block plan transmission until ‘Approved’ status is set.” STPA identified 142 Unsafe Control Actions, including things related to the timing of image acquisition (“too long after immobilization”) that HFMEA missed because HFMEA focuses on the step being done, not the temporal relationship between steps.

Link to Source

Blood Gas Analyzer: A Two-Week STPA Found the Recall Cause That a Year of FMEA Missed

A blood gas analyzer was recalled because of a safety defect. The manufacturer’s team spent a year performing FMEA and identified 75 hazardous scenarios. None of them explained the issue that caused the recall. A single analyst, identifying the control loops within the device, found 175 scenarios in two weeks. Included in these 175 was the specific interaction scenario that led to the recall. STPA found more scenarios in less time.

A more thorough analysis is often assumed to take longer. STPA works top-down from a model of the control structure, so the analysis starts at the interactions between controllers, where problems like this one tend to arise, without first working through the components one by one.

Link to Source

Benefit 2 · Evidence

STPA Takes Less Time to Apply

U.S. Missile Defense Agency Finds More Hazards in Less Time with STPA than Traditional Methods

U.S. Missile Defense Agency (MDA) published findings from applying STPA to the Ballistic Missile Defense System (BMDS). The STPA effort was conducted by two people over three months. The usual MIL-STD-882 methods (FMEA, FTA, etc.) required over a dozen specialists working for over a year to complete the safety assessment. In hours, the STPA took about 960 and the traditional approach (FMEA, FTA, and others) about 28,800, about a thirtieth of the effort.

Link to Source

Blood Gas Analyzer: Two Weeks of STPA, After a Year of FMEA

A blood gas analyzer was recalled because of a safety defect. The manufacturer’s team spent a year performing FMEA and identified 75 hazardous scenarios. None of them explained the issue that caused the recall. A single analyst, identifying the control loops within the device, found 175 scenarios in two weeks. Included in these 175 was the specific interaction scenario that led to the recall. STPA found more scenarios in less time. A more thorough analysis is often assumed to take longer. STPA works top-down from a model of the control structure, so the analysis starts at the interactions between controllers, where problems like this one tend to arise, without first working through the components one by one.

Link to Source

Fatima: STPA Found the Missing Control Logic in Under a Day

Fatima Company performed a rigorous HAZOP by an experienced team, requiring months of effort. Despite this, an incident occurred due to missing control logic. They began a research project to determine whether other methods could be better suited. They asked a team that was unfamiliar with the incident or the flaw to apply STPA and look for any potential weaknesses. In less than a day, the STPA team identified the missing control logic that had led to the incident. The HAZOP had taken more than 30 times as long.

Link to Source

Cooling System: The Effort Each Method Took

An extensive comparison study was performed on a product’s cooling system. Independent teams were asked to apply different methods to look for flaws in the design and requirements.

• FMEA: A team of professionals spent over 1,000 person-hours creating 200+ pages of FMEA documentation to fully analyze the system.
• FTA: A team of professionals spent weeks developing and reviewing detailed fault trees for the system.
• HAZOP: A team of professionals spent 120 person-hours completing a HAZOP study of the system.
• STPA: A team of professionals analyzed the system using STPA. The teams required between 1 and 32 person-hours to apply STPA. Some teams only had a few hours of STPA training and no previous experience using STPA.

Every STPA team finished faster than the teams using the other methods. At $75 an hour, the STPA cost about $2,400 and found a design flaw that would have cost at least $1 million, a return of at least 416 to 1. The source cautions that these figures come from one experiment and are not a recommendation for how long an STPA should take.

Link to Source

General Motors: Missing Requirements Found Earlier and More Efficiently

General Motors (GM) reported that STPA provided requirements “more efficiently” and found missing requirements early in the concept phase. Missing or flawed requirements are a leading cause of software-related accidents. Verification checks whether software meets its requirements, and STPA asks whether the requirements themselves are safe.

Link to Source

Valeo Range Extender: Constraints the Other Methods Missed, with a Third of the Effort

Valeo conducted a comparative study on STPA and FTA. The study compared the effort required to perform STPA against the combined effort of Fault Tree Analysis (FTA) and Critical Path Analysis (CPA). The traditional FTA/CPA process required three times the effort (person-hours) of the STPA analysis. With three times the effort, the CPA and FTA did not produce the two safety constraints that STPA allocated to the inverter control software. Two features of the system account for the difference. The system involved “Shared control with inverter software” and “One controller on two processes.” Modeling these shared dependencies in a Fault Tree requires complex Boolean logic structures that are time-consuming to build and verify. In STPA, the same arrangement is a control structure with two arrows, and the analysis can turn straight to conflicting commands. The system lacked a physical torque sensor, relying instead on “Software complexity to estimate torque.” FMEA has difficulty analyzing estimation algorithms, because they have no physical component that can break. STPA asks about process model flaws (for example, the software believes torque is X when it is actually Y), which leads the analysis to these software logic hazards.

Link to Source

JAXA H-II Transfer Vehicle: Two Weeks of STPA, Compared with Months of Fault Tree Analysis

The Japan Aerospace Exploration Agency (JAXA) applied STPA and evaluated its efficiency against NASA-mandated Fault Tree Analysis. The STPA analysis was performed by 1-2 people in two weeks. The traditional safety analyses took teams of engineers months, around 30 times the effort. The STPA identified everything in the official Fault Tree Analysis, along with causal factors that the fault tree had not identified.

Link to Source

Embraer Identifies More Hazards per Engineering Hour with STPA than with Traditional Methods

Embraer applied STPA in developing aircraft systems, such as the Smoke Control System and the Air Management System. The STPA took 3.5 months, less time than the other techniques, and produced many recommendations and low-cost opportunities to improve safety that were missed by standard approaches (FHA, FMEA, FTA, etc.)

Link to Source

Benefit 3 · Evidence

STPA Finds Flaws Earlier, Minimizing the Cost to Fix Them

Embraer: Findings Made Earlier in Design

What Embraer’s Comparison Found
  • Early Detection: 19% of the STPA findings came earlier than they otherwise would have, when design changes cost less.
  • Standard Process Comparison: The existing standard processes captured 44% of the STPA safety findings.

Link to Source

General Motors: Missing Requirements Found in the Concept Phase

General Motors (GM) reported that STPA provided requirements “more efficiently” and found missing requirements early in the concept phase. Missing or flawed requirements are a leading cause of software-related accidents. Verification checks whether software meets its requirements, and STPA asks whether the requirements themselves are safe.

Link to Source

Automated Vehicles: STPA in the ISO 26262 Concept Phase

Abdulkhaleq et al. examined how STPA relates to the ISO 26262 safety standard and Hazard Analysis and Risk Assessment (HARA), including FTA, FMEA, etc. The study found that applying STPA upfront before other methods, specifically during the Concept Phase, provided a better way to achieve the objectives of the Functional Safety Concept. While traditional HARA focuses on classifying hazardous events based on severity, exposure, and controllability, STPA identifies the specific causal scenarios, even with limited design details and before anything is known about failures, their exposure, or their likelihood. The team concludes that it is advantageous to apply STPA with “a little bit knowledge about the detailed design of the system at early stages”. Applied in the concept phase, STPA can define safety constraints for automated functions before the vehicle’s distributed architecture is fixed.

Link to Source

Air Traffic Management: Safety Constraints Before the Technology Is Chosen

Justin Poh’s 2025 MIT dissertation applies STPA to air traffic management for urban air mobility (UAM), at a high level of abstraction. The analysis identifies unsafe control actions such as “Air Traffic Management does not coordinate the interaction between two UAM aircraft or a UAM aircraft and another airspace user when a collision between them is imminent.” This identification leads to the derivation of safety constraints (requirements) that the eventual system architecture must satisfy. This process occurs long before other safety/reliability methods are used, before the engineers have decided on the specific radar technologies, communication protocols, or software platforms that will be used. The architecture is then designed to meet those constraints, so safety is built into the design rather than inspected in at the end.

Link to Source

Part 4 · Making the Case

The Cost of Finding Flaws Late

STPA finds flaws and defects earlier, reducing the cost of fixes.

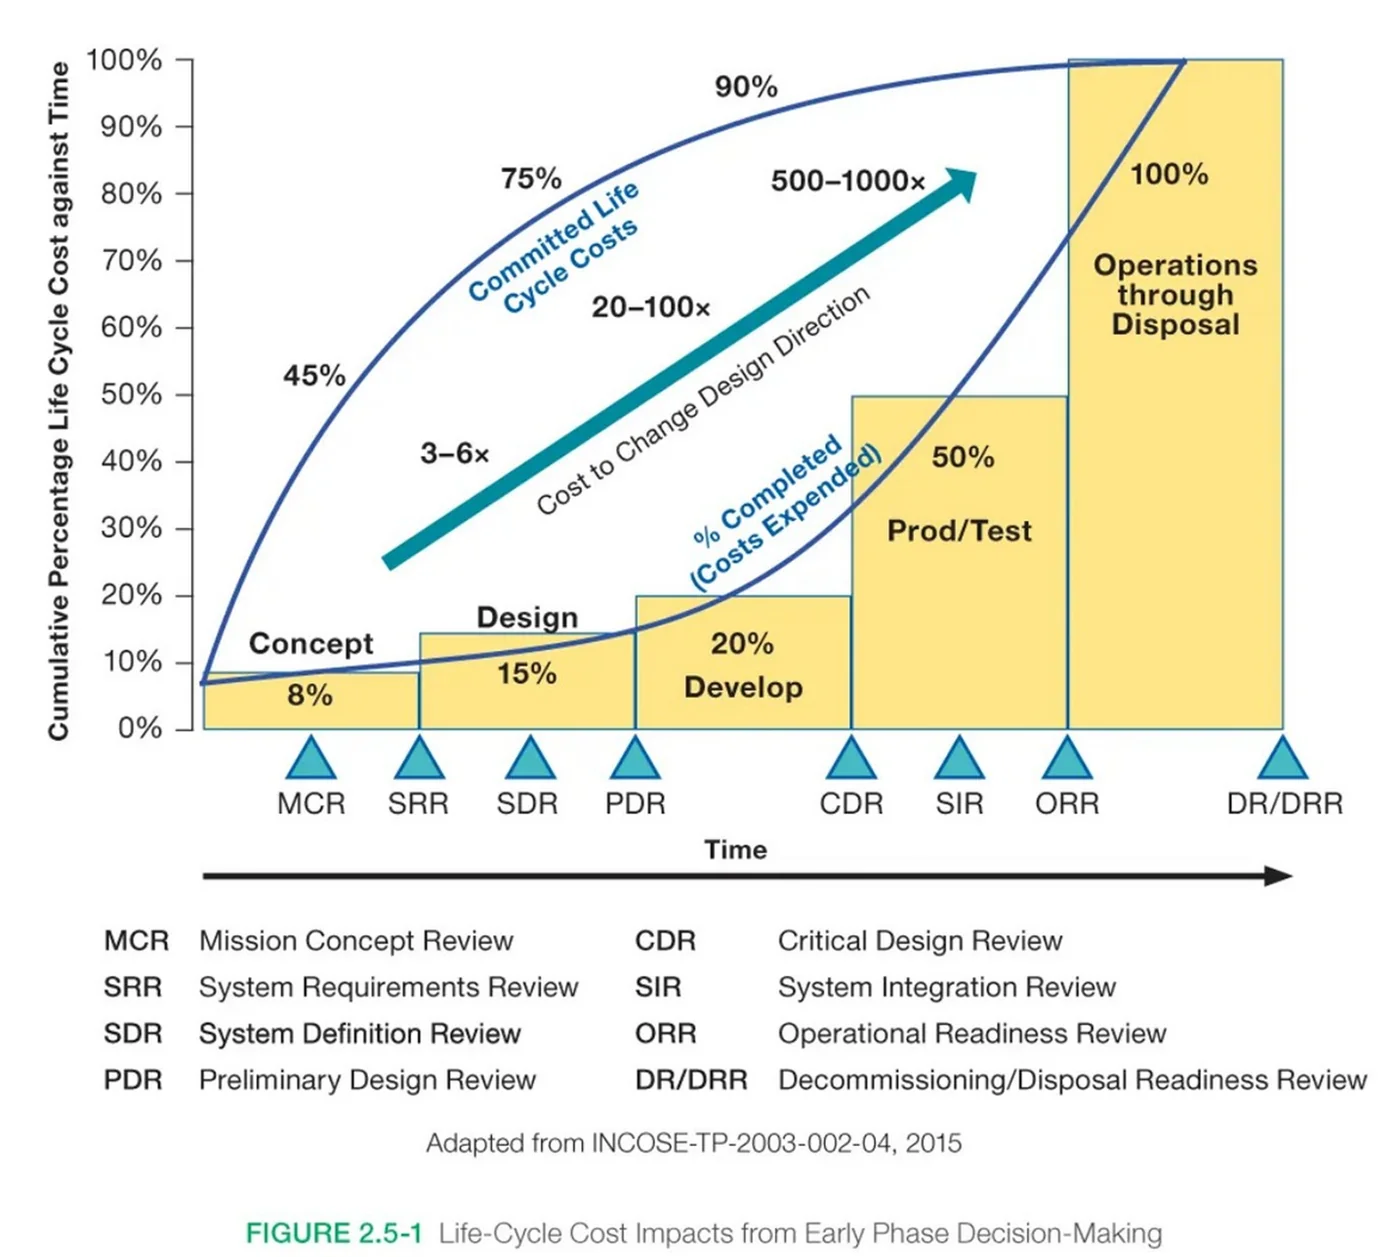
Life-Cycle Cost Impacts from Early Phase Decision-Making

NASA Figure 2.5-1, Life-Cycle Cost Impacts from Early Phase Decision-Making: most life-cycle costs are committed during the concept and design phases, long before they are spent, and the cost to change the design rises from 3–6× to 20–100× and then 500–1000× as the project moves through its phases.

The cost to fix a defect or change a requirement grows steeply as a project moves forward. As shown in NASA’s Cost Effectiveness study (Fig 2.5-1), a change that costs $1 to fix during the Requirements phase can cost $100 or more once the system reaches the Development or Operations phase.

Many of the studies on this page found flaws that the other methods missed. A flaw like that is found in one of two ways:

  1. Early, by analysis in the concept and design phases, when a fix costs least.
  2. Late, when the flaw turns up during integration, testing, or operation, where a fix costs far more, or after an accident.

On NASA’s figures, the same change costs orders of magnitude less in the concept phase than in operation. Teams can apply STPA in the concept phase, before the design is detailed, and fix the flaws they find while changes still cost little.

Adapted from INCOSE-TP-2003-002-04, 2015

NASA Systems Engineering Handbook, section 2.5, Cost-Effectiveness Considerations

Part 5 · Making the Case

Briefing Your Leadership

If you are preparing to brief your leadership, check the generic slides below that explain some of the fundamental reasons for using STPA.

Tailored Leadership Briefing

We offer customized briefings to introduce STPA to your organization or leadership as one of our professional services. Contact us to schedule a session.

Request a Tailored Leadership Briefing

Where to Go Next

Keep Learning

The introductions to the methods, the evidence for using them, and the industry pages are all free.

STAMP Resources

Take a Class

Self-paced online courses and live classes, with certification for those who want it.

See the classes

Get Help on a Project

We work alongside teams applying STPA or CAST to their own systems.

About project support

Questions? Email [email protected].